





The aim of this study was to assess the feasibility and inter-rater reliability of a set of 22 quality indicators and to identify quality problems in the clinical practice of hospital-based physical therapy units.
MethodsAn observational, descriptive, cross-sectional, multicentre study with a mixed approach was conducted in three hospitals in Spain. Twenty-two indicators (nine management and thirteen clinical) were evaluated and refined according to the feasibility of the available data, and interobserver agreement (inter-rater reliability) was measured. The analysis combined qualitative and quantitative methods.
ResultsOf the 22 quality indicators, 13 were feasible and showed concordance between evaluators across all hospitals included in the study. The main difficulties the evaluators observed were: inadequate identification of the pathologies of interest, limited identification of the initial diagnosis or index episode in patients with chronic conditions, and failure to record essential evaluation information. Opportunities for improvement include enhancing the detailed assessment of therapeutic objectives, providing early care for stroke patients, and clearly prescribing exercise treatment.
ConclusionA total of 13 quality indicators (9 clinical and 4 management indicators) were feasible and reliable. The remaining 9 were refined to assess those units that so request. The quality levels, along with analyses of feasibility and inter-rater reliability, provided relevant information on the performance of the physical therapy service across three hospitals. Implementing this set of indicators provides hospitals with a systematic evaluation tool that promotes improvements in care quality and organizational learning.
In the discipline of physical therapy, there is currently no agreed-upon conceptual framework for quality of care. Although some attempts have been proposed by Steenbruggen et al.1 and the World Confederation for Physical Therapy,2 these frameworks still lack further development in terms of operationalization and alignment with the more established conceptual models used in medicine and nursing.3
This disadvantage is even more concerning in hospitals and primary care centres, where quality management is the language used by managers and, ultimately, the means to provide a methodology for continuous improvement and to be accountable to other professionals and society.
To advance the implementation of a quality management model applicable across the discipline of physical therapy, physical therapists need quality indicators (QIs) to quantify performance and outcomes related to care aspects against an evidence-based standard that specifies quality and its dimensions.4 Regarding these indicators, there are a number of initiatives at national levels that have proposed sets for specific areas such as chronic care,5 patient safety or quality management in a broader sense. 6,7
With the aim of addressing the previously mentioned relative lack of knowledge of quality management in physical therapy, a pioneering research project was launched in 2018 at the hospital level in Spain. This was based on the work of a group of supervisors from the same region and expert researchers in healthcare quality,8 and 22 indicators were created: 13 of them clinical (3 for therapeutic objectives, 3 for neurological conditions, 4 for musculoskeletal conditions, 2 for respiratory diseases, and 1 for the over-65s), and 9 for the management of the physical therapy unit. The aim of this study was to assess the feasibility and inter-rater reliability of this set of QI, as well as to identify quality problems within the clinical practice of evaluated hospital-based physical therapy units.
MethodsStudy designA multicenter mixed-methods study was performed, in which 22 indicators of quality of care in hospital-based physical therapy –previously selected from a systematic review8– were sequentially tested and refined. The design of this multi-stepped mixed-methods study was observational, descriptive, and cross-sectional in each study site. The feasibility of the 9 management indicators was tested based on the availability of existing data sources and the time used to measure a single case. Whilst we evaluated the 13 clinical indicators for their measurability (feasibility) and their inter-rater agreement (i.e., their reliability), following the GRRAS guidelines.9
Selection and recruitment of participating centersThree hospitals were selected by convenience recruitment criteria, which were based on: a) the availability and willingness of the heads of physical therapy departments to collaborate; b) their location in three different regions of public hospitals of Spain within the Spanish National Health System (SNHS), with decentralized and autonomously managed governance and provision of health services. Consequently, they differed in aspects such as data registration systems, the organization of rehabilitation and physical therapy units, and the functional role of physical therapy supervisors.
The study was approved by the ethics committees of Hospital Universitario Reina Sofía (Ref. 313/10-11-21), Hospital Universitario Fundación Alcorcón (Ref. 21/162), and Hospital El Bierzo (Ref. 21155). In addition, these approvals were ratified by the Ethics Committee of the Universidad Católica San Antonio de Murcia (UCAM).
Sample sizeThe sample size for clinical indicators, which measure healthcare processes, was determined using the following formula:10 n=(z2×p×(1−p))i2 where z = 1.96, i is the precision interval (0.15) and p is the expected proportion of compliance (0.5)10 The sample size was estimated at 43 observations per indicator. We randomly selected 60 cases (allowing oversampling in the event of substitution) from each study population, as presented in the indicator reference sheets (Appendix A).
Unit management indicators were intended to be measured directly from readily exploitable or accessible records to the physical therapy supervisor. No sampling was required.
Identification and sampling method of the study populationPatients were identified using ICD-10 codes recorded in the Spanish Minimum Basic Data Set (MBDS), according to each indicator's requirements, including both inpatients and outpatients. Systematic random sampling was used.
Data collectionTo assess and measure the performance (quality level) of the 13 clinical indicators, clinical records (electronic or paper medical records) were used, along with additional auxiliary records. This data collection was performed by two independent, non-unique external evaluators to the hospitals, using standardized ad hoc formats: an Excel spreadsheet for clinical indicators (Appendix B) and a Google Form for management indicators (Appendix C). Evaluators were asked to keep a personal log, in the form of a journal, to record the difficulties and concerns they experienced, as well as to identify the optimal documents and information routes.
Instruments calibrationDuring testing, indicator wording and assessment criteria were iteratively refined. When possible, optimal data flows and adjusted data collection tools were implemented to address collection challenges and inter-rater discrepancies. These modifications were applied post-evaluation to preserve evaluator independence.
Data synthesis and analysisBoth feasibility and inter-rater reliability were quantitatively and qualitatively. Feasibility was categorized into five groups: 1a. High (Available in all hospitals and without high cost); 1b. Moderate (Available in all hospitals but requiring high cost); 2a. Low (Available in at least one hospital, without high cost); 2b. Very low (Available in at least one hospital, but requiring high cost); 3. Not feasible/not measurable.
Evaluators took personal notes in a diary. Any situation that prevented or hindered the assessment of indicators during data extraction was recorded, and the estimated time required to measure one case for each indicator was also recorded. High cost occurred when the data needed to be searched across more than 3 documents, the language was not standardized, or the time per case exceeded 30 minutes. At the end of the data collection, evaluators discussed the difficulties observed and concerns experienced, classified them, and described them.
Inter-rater reliability was tested by means of the percentage of observed agreement between the two evaluators (NI and BA-C) and the calculation of the inter-observer kappa index (κ) for each indicator measured in clinical records. Since κ values can be severely affected by the observed prevalence of the classification categories and assessment biases, the Prevalence-Adjusted Bias-Adjusted Kappa (PABAK) was calculated. Both indices were interpreted using the criteria of Landis and Koch described in 1977,11 allowing decisions to be made based on the results for each study site. Inter-rater reliability was dichotomized (PABAK ≥ 0.7) to determine which hospitals were reliable and which were not. Finally, to identify areas of opportunity, the quality level (compliance and 95% confidence interval) of each indicator and sub-indicator was estimated. All calculations were performed in Excel spreadsheets.
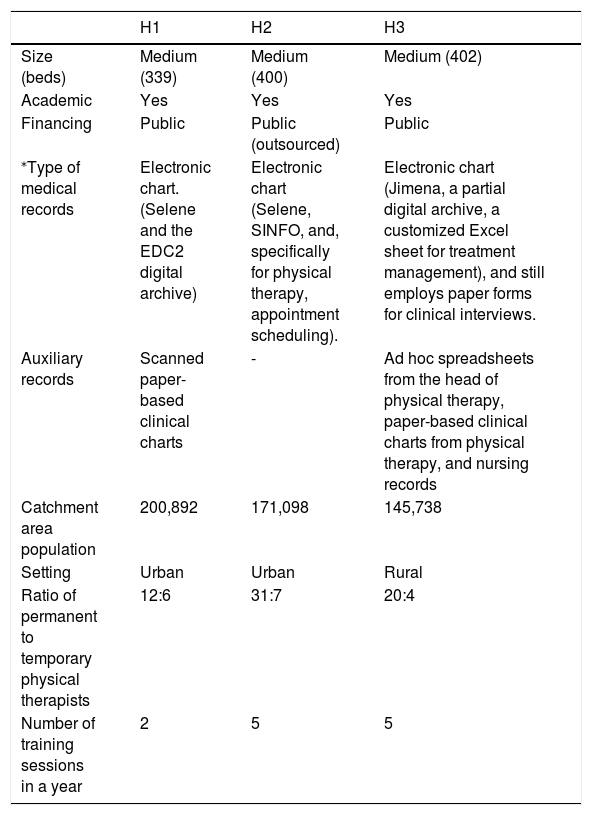
ResultsThe study locations and their characteristics are described in Table 1. Each study location used a different electronic clinical chart system. Data collection for the indicators took place during the first half of 2022.
Description of the study locations and their characteristics.
| H1 | H2 | H3 | |
|---|---|---|---|
| Size (beds) | Medium (339) | Medium (400) | Medium (402) |
| Academic | Yes | Yes | Yes |
| Financing | Public | Public (outsourced) | Public |
| ⁎Type of medical records | Electronic chart.(Selene and the EDC2 digital archive) | Electronic chart (Selene, SINFO, and, specifically for physical therapy, appointment scheduling). | Electronic chart (Jimena, a partial digital archive, a customized Excel sheet for treatment management), and still employs paper forms for clinical interviews. |
| Auxiliary records | Scanned paper-based clinical charts | - | Ad hoc spreadsheets from the head of physical therapy, paper-based clinical charts from physical therapy, and nursing records |
| Catchment area population | 200,892 | 171,098 | 145,738 |
| Setting | Urban | Urban | Rural |
| Ratio of permanent to temporary physical therapists | 12:6 | 31:7 | 20:4 |
| Number of training sessions in a year | 2 | 5 | 5 |
H: Hospital
H1: Hospital Universitario Reina Sofía de Murcia; H2: Hospital Fundación Universitario de Alcorcón; H3: Hospital Universitario El Bierzo
Jimena is a plataform designed for the automatic capture and recording of clinical data.
EDC2: Virtual platform that supports the storage and registration of scanned paper-based reports.
SINFO is a platform designed for the automatic capture and recording of clinical data.
EDC2: Virtual platform that supports the storage and registration of scanned paper-based reports.
Of the 22 indicators, 17 were feasible in at least two hospitals and 13 in all hospitals (Table 2). Hospital 1 had the greatest difficulty measuring the indicators (feasibility problems).
Overview of the feasibility (dichotomized) and part of the inter-rater reliability in the three hospitals under analysis.
H1: Hospital; Universitario Reina Sofía de Murcia; H2: Hospital Fundación Universitario de Alcorcón; H3: Hospital Universitario El BierzoH1: Hospital Universitario Reina Sofía de Murcia; H2: Hospital Fundación Universitario de Alcorcón; H3: Hospital Universitario El Bierzo
1a – High feasibility. Available in all hospitals at no extra cost.
1b – Moderate feasibility. Available in all hospitals, but at a high cost.
2a – Low feasibility. Available in at least one hospital at a reasonable cost.
2b – Very low feasibility. Available in at least one hospital but requiring high cost.
3 – Not feasible/not measurable.
The main difficulties identified by the evaluators can be summarized as follows: inadequate identification of the pathologies of interest due to ICD codes lacking specificity; limited identification of the initial diagnosis or index episode in patients with chronic conditions; and failure to record essential evaluation information. Detailed qualitative information for each indicator and sub-indicator is provided in Appendix D. The clinical indicators that were not feasible in any hospital were indicators 1.2 and 1.3 on achieving treatment goals and the percentage of follow-up visits once achieved, and 3.3 on patients newly diagnosed with rheumatoid arthritis. Among the management indicators, the two non-feasible indicators were 6.3, sessions lost due to transport, and 6.8, readmission within 90 days for patients referred to outsourced care or non-public services.
Regarding the three indicators of therapeutic objectives, following indicator 1.1, there was practically no objective recorded. Meanwhile, as with the other indicators focusing on respiratory diseases (4.1 and 4.2), the indicator for rheumatoid arthritis was hampered by difficulties in identifying the onset of a diagnosis or episode and by unspecified ICD codes. In the case of the two non-feasible management indicators, the lack of recorded data needed to collect or calculate them is worth noting.
Finally, after assessing each study location, major adjustments were made to the non-feasible indicators. Most notable was the reformulation of indicator 6.8 (Rate of patients referred with readmission within 90 days due to unresolved problem), now simplified to ‘Rate of patients referred to private healthcare’ and targeted at specific population groups.
Inter-rater reliabilityHospital 1 was the site where the fewest indicators could be measured and where the greatest differences in evaluator agreement were observed. This was progressively reduced in the following locations. There was only one criterion with a PABAK of 0.0 (‘at least one therapeutic objective’ criterion) due to disagreements regarding what constituted a complete therapeutic objective and the diversity of formats to collect that information. The remaining indicators and most of the other criteria (sub-indicators) achieved acceptable PABAK values (median 0.95, interquartile range 0.91-1). All the observed concordance, kappa, and PABAK values are available in Appendix E, while the qualitative analysis of the discordance between evaluators is summarised in Appendix F.
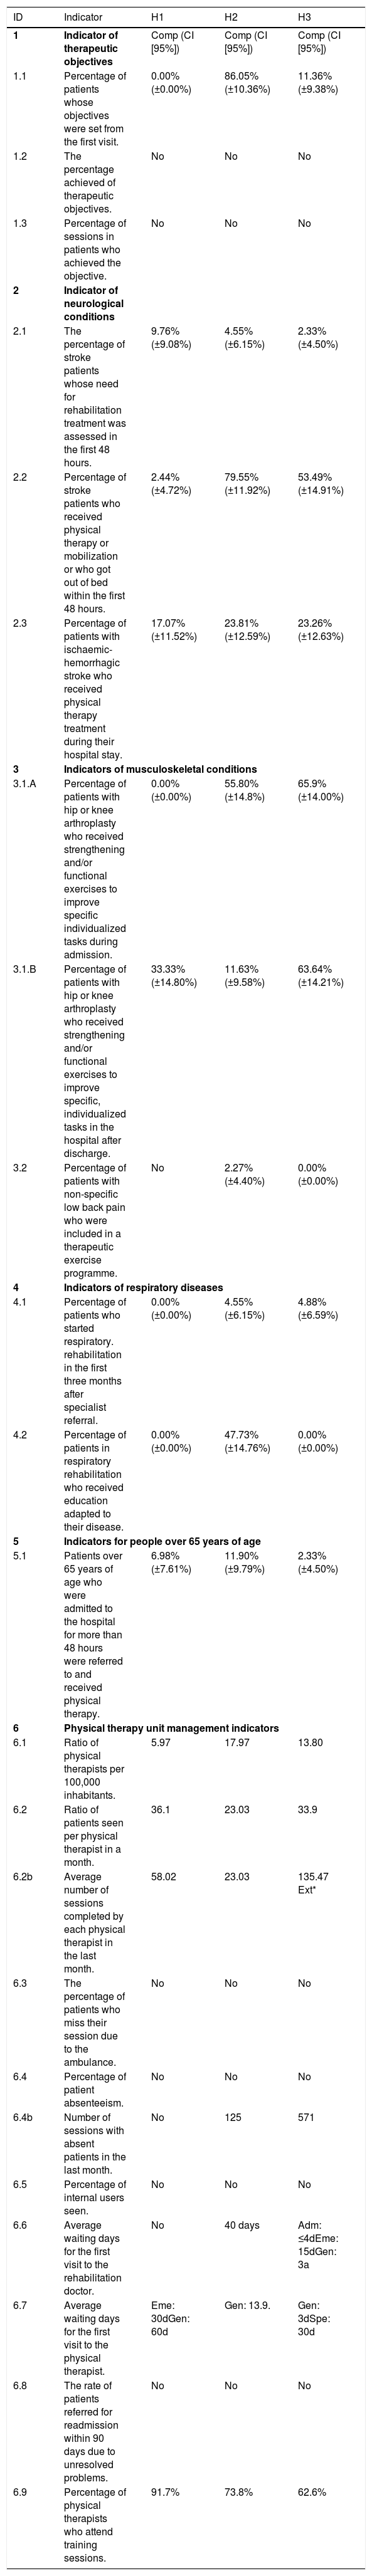
Healthcare quality levelTable 3 describes the quality level of the indicators and their measurable sub-indicators. H1 had the lowest compliance levels. The indicators that were met by more than 75% were indicator No. 1.1 (86.05% ± 10.36%) and indicator No. 2.2 (79.55% ± 11.92%) in H2, with relatively narrow 95% CIs indicating precise estimates of compliance. There were four indicators below 5% in H1 (2.2, 3.1.A, 4.1, 4.2), four in H2 (1.1, 2.1, 3.2, 4.1), and five in H3 (2.1, 3.2, 4.1, 4.2, 5.1). Table 3 shows the differences in the management indicators results across the 3 hospitals.
Healthcare quality level. Compliance level of clinical indicators and results from management indicators.
| ID | Indicator | H1 | H2 | H3 |
|---|---|---|---|---|
| 1 | Indicator of therapeutic objectives | Comp (CI [95%]) | Comp (CI [95%]) | Comp (CI [95%]) |
| 1.1 | Percentage of patients whose objectives were set from the first visit. | 0.00%(±0.00%) | 86.05% (±10.36%) | 11.36%(±9.38%) |
| 1.2 | The percentage achieved of therapeutic objectives. | No | No | No |
| 1.3 | Percentage of sessions in patients who achieved the objective. | No | No | No |
| 2 | Indicator of neurological conditions | |||
| 2.1 | The percentage of stroke patients whose need for rehabilitation treatment was assessed in the first 48 hours. | 9.76%(±9.08%) | 4.55%(±6.15%) | 2.33%(±4.50%) |
| 2.2 | Percentage of stroke patients who received physical therapy or mobilization or who got out of bed within the first 48 hours. | 2.44%(±4.72%) | 79.55% (±11.92%) | 53.49% (±14.91%) |
| 2.3 | Percentage of patients with ischaemic-hemorrhagic stroke who received physical therapy treatment during their hospital stay. | 17.07% (±11.52%) | 23.81% (±12.59%) | 23.26% (±12.63%) |
| 3 | Indicators of musculoskeletal conditions | |||
| 3.1.A | Percentage of patients with hip or knee arthroplasty who received strengthening and/or functional exercises to improve specific individualized tasks during admission. | 0.00%(±0.00%) | 55.80%(±14.8%) | 65.9%(±14.00%) |
| 3.1.B | Percentage of patients with hip or knee arthroplasty who received strengthening and/or functional exercises to improve specific, individualized tasks in the hospital after discharge. | 33.33% (±14.80%) | 11.63%(±9.58%) | 63.64% (±14.21%) |
| 3.2 | Percentage of patients with non-specific low back pain who were included in a therapeutic exercise programme. | No | 2.27% (±4.40%) | 0.00% (±0.00%) |
| 4 | Indicators of respiratory diseases | |||
| 4.1 | Percentage of patients who started respiratory. rehabilitation in the first three months after specialist referral. | 0.00% (±0.00%) | 4.55% (±6.15%) | 4.88% (±6.59%) |
| 4.2 | Percentage of patients in respiratory rehabilitation who received education adapted to their disease. | 0.00% (±0.00%) | 47.73% (±14.76%) | 0.00% (±0.00%) |
| 5 | Indicators for people over 65 years of age | |||
| 5.1 | Patients over 65 years of age who were admitted to the hospital for more than 48 hours were referred to and received physical therapy. | 6.98% (±7.61%) | 11.90% (±9.79%) | 2.33% (±4.50%) |
| 6 | Physical therapy unit management indicators | |||
| 6.1 | Ratio of physical therapists per 100,000 inhabitants. | 5.97 | 17.97 | 13.80 |
| 6.2 | Ratio of patients seen per physical therapist in a month. | 36.1 | 23.03 | 33.9 |
| 6.2b | Average number of sessions completed by each physical therapist in the last month. | 58.02 | 23.03 | 135.47 Ext* |
| 6.3 | The percentage of patients who miss their session due to the ambulance. | No | No | No |
| 6.4 | Percentage of patient absenteeism. | No | No | No |
| 6.4b | Number of sessions with absent patients in the last month. | No | 125 | 571 |
| 6.5 | Percentage of internal users seen. | No | No | No |
| 6.6 | Average waiting days for the first visit to the rehabilitation doctor. | No | 40 days | Adm: ≤4dEme: 15dGen: 3a |
| 6.7 | Average waiting days for the first visit to the physical therapist. | Eme: 30dGen: 60d | Gen: 13.9. | Gen: 3dSpe: 30d |
| 6.8 | The rate of patients referred for readmission within 90 days due to unresolved problems. | No | No | No |
| 6.9 | Percentage of physical therapists who attend training sessions. | 91.7% | 73.8% | 62.6% |
H: Hospital; H1: Hospital Universitario Reina Sofía de Murcia; H2: Hospital Fundación Universitario de Alcorcón; H3: Hospital Universitario El Bierzo. Comp: Compliance, CI [95%]: Confidence Interval, No: Could not be measured, Adm: Admitted, Eme: Emergency, Gen: General, Spe: there is more waiting list in cases of specialities such as lymphoedema or stress retraining, d: days, y: years.
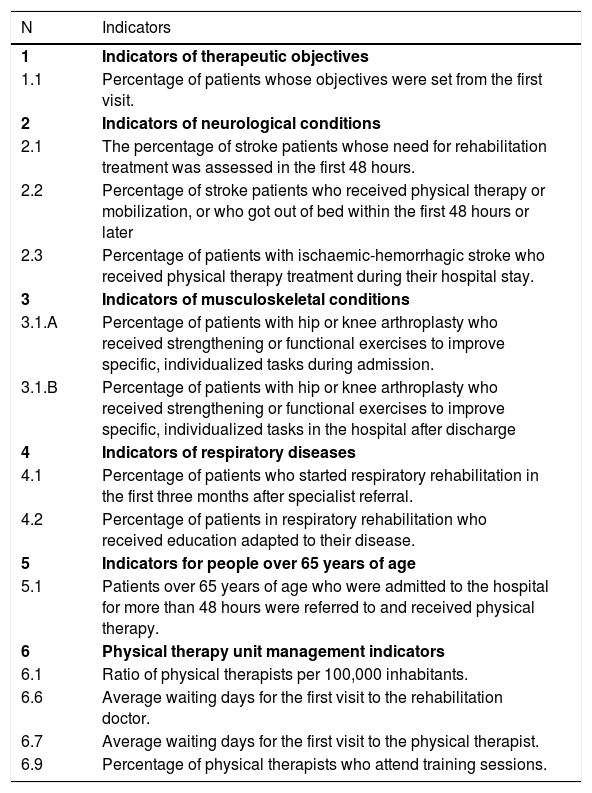
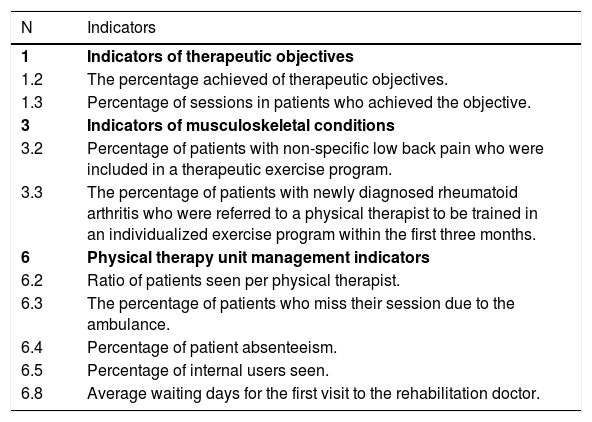
Two groups of indicators are established from our results. The first group consists of 13 indicators (9 clinical and 4-unit management indicators) that have been shown to be measurable and reliable in this study (Table 4). The second includes the 9 indicators that could not be proven sufficiently reliable or measured, at least not without incurring high measurement costs, during the study (Table 5). Data collection tools and QI were refined as each hospital was surveyed. Final indicator sheets and final data collection tools are available in Appendices A, B, and C, respectively.
Set of indicators for continuous monitoring and comparative use: considered feasible and reliable (feasibility categories 1a, 1b, and 2a, which have obtained an inter-rater reliability value>0.7 of PABAK in at least 2 hospitals).
A set of indicators for punctual evaluation or internal monitoring is to be refined to ensure feasibility and reliability.
The evaluation found nine clinical and four management indicators to be feasible and reliable. The remaining nine indicators are usable but require further adaptation and testing to ensure their inter-rater reliability and feasibility in the settings where they will be used.
Our comprehensive analysis helped validate the evaluation tools, reducing variability due to individual evaluator interpretations. Additionally, the iterative modifications improved the efficiency and quality of data extraction from clinical records and facilitated the development of a template for the systematic collection of indicators.
Measured indicators revealed discrepancies between the expected clinical practice and the care actually delivered in each hospital, based on a thorough review of clinical records conducted by two independent reviewers. The comparison among the three physical therapy units enabled the identification of their specific strengths and areas for improvement, while providing an overall characterization of these services despite the study's methodological limitations.
Therefore, this study revealed critical opportunities for improvement, either when indicators could not be measured –highlighting limitations in data availability and health information system structure– or because their point estimates and their CI indicated low levels of quality of care. These findings point to areas where targeted actions may enhance the performance and quality of physical therapy services within each hospital. Notable low compliance with therapeutic objective setting was observed in two hospitals, partly because the software or computer programs used to record these objectives were not designed with specific sections for physical therapists to add this data. A recent national survey emphasized the difficulties physical therapists face when discussing treatment goals with their patients.12 Establishing this initial goal is essential for shared decision-making,13 which, along with the use of appropriately selected patient-reported outcome measures (PROMs), contributes to both the effectiveness of the therapeutic partnership and the patient's self-efficacy.14 Moreover, failing to document treatment goals constitutes a serious legal and ethical breach that could affect continuity of care.15
Regarding the referral time for patients with respiratory pathology to physical therapy, we found a notable lack of compliance with quality-of-care levels in the population with chronic obstructive pulmonary disease, despite several international indicators16 specifying a maximum of three months from diagnosis to commencement of physical therapy.17 The disease-specific education patients receive is suboptimal in two of the three hospitals evaluated, despite clear evidence that self-management training significantly enhances patient involvement and disease control, helping patients acquire skills such as symptom recognition and exercise levels.18
Similarly, our results concerning stroke patients indicated a low prevalence of physical therapy interventions, which could be affected by limited accessibility. This is a striking result, even though this is a priority in most health systems, given its increasing prevalence19 and the existence of international consensus recommendations that advocate for early access to physical therapy, which facilitates recovery, prevents complications, and readmissions.20,21
Our research also highlights a low representation, or near absence, of the physical therapy received by the over-65 group of patients, who may suffer from the inability to regain functionality, adapt to new circumstances, or an increased likelihood of hospital readmission, all of which contribute to bad patient outcomes and elevated healthcare costs.22–25 The high exposure to deconditioning and frailty of this population underscores the urgent need for physical therapy evaluation, treatment, and follow-up upon admission.
In sum, our data highlight the absence of standardized physical therapy treatments for several patient groups, pointing to significant safety risks and critical barriers to providing high-quality physical Therapy care. One of the main factors contributing to delays in the provision of physical therapy—or its omission altogether— as indicated by several of the analyzed indicators, is the low referral rate from medical specialists other than rehabilitation physicians (e.g., neurologists, traumatologists, internists). In this regard, widespread adoption of new care models that enhance access to physical therapy is crucial.26 The American Physical Therapy Association (APTA) supports direct access to physical therapy, which could reduce delays and healthcare costs and alleviate patient frustration.27–29
Developing advanced training and specialties within the profession may enhance direct access to physical therapy, thereby alleviating workload pressure. There is a considerable percentage of Spanish physical therapists with postgraduate training (34.7%);12 however, this resource is underutilized within the SNHS. Integrating qualified professionals into hospital units, along with effective resource management by healthcare administrators, could facilitate this new model of direct referral.30,31
Quality indicators are crucial for managers and decision-makers in integrating physical therapy services with the rest of the hospital teams. Greater efforts from supervisors, administrative staff, and clinical staff are needed to systematically document all healthcare processes in standardized, streamlined records. These records must be integrated with the rest of the multidisciplinary team to ensure continuous, high-quality care.32,33 However, there are a few adequately assessed indicators in the literature,8 which hampers their adoption, while several authors have already emphasized the urgent need to incorporate QI for physical therapy across various contexts.4,34
This situation reflects the limited methodological rigor and still-limited culture of using these tools to improve healthcare quality in our profession.35–37 The level of adoption of physical therapy-related QI in the SNHS is not an exception and remains low. Effective implementation of quality monitoring depends significantly on empowering physical therapy managers and fostering a culture of quality improvement. Fortunately, this work and other international efforts are underway,38 aiming to establish quality measures applicable in hospital-based physical therapy units.
Finally, the results of this study highlight the importance of not only recording inpatient activity but also systematically documenting outpatient care and the specific processes performed in hospital-based physical therapy units. The identified gaps depend on appropriate and standardized health information systems (e.g., optimal coding for adequate pathology identification, enhanced therapeutic goal tracking), which may limit not only the implementation and scaling-up of these measures but also compromise the inter-rater reliability of quality measurements. Therefore, the lack of structured data-collection procedures impedes the ability to monitor the quality of care, plan resources, and identify opportunities for improvement. Strengthening registration systems for outpatient and inpatient procedural activity is therefore essential to ensure that physical therapy services are visible, measurable, and accountable within the broader healthcare system.
Implications for practiceOur indicators enable the assessment of coordination and resources in hospital physical therapy units, supporting internal analysis and inter-hospital comparison to foster organizational improvement.
This study tested 17 indicators across three public hospitals within the SNHS. These indicators can be immediately incorporated into a dashboard to improve the management of physical therapy units,39 covering both administrative and clinical aspects. Further studies might narrow the focus to assess the detected needs of local physical therapy units more comprehensively and specifically.40,41 Using these indicators, physical therapists can enhance their clinical care and adhere to current facility-level healthcare decision-making and management. There remains a substantial opportunity for physical therapy units to demonstrate the added value of their work and contributions to both other health disciplines42 and the general population.43
Implications for researchThe selected indicators may be complemented by context-specific or population-focused measures, including structural or outcome indicators (e.g., research activity, protocol availability, or relevant health outcomes), aligning with the RECAL project evaluations of the SNHS.44
LimitationsOur study has some limitations. Firstly, we acknowledge that our feasibility results are context-dependent and primarily depend on the availability of high-quality, well-structured information and the capabilities to exploit it. There is no guarantee that the indicators we identified as feasible are measurable in every hospital. The study locations may not be representative of the characteristics of every Spanish public hospital. Although the findings may not represent all Spanish public hospitals, the study included hospitals from different administrative regions, reflecting diverse health information systems and data sources, thereby increasing the generalizability of the results. This diversity was considered in the assessment of feasibility and inter-rater reliability to adapt collection tools to different contexts and a wider range of evaluation circumstances.
Nevertheless, variability in clinical documentation practices and registry structures across Spain may still limit the generalizability of the results. Secondly, the estimated quality levels are partly influenced by inter-rater agreement in applying certain indicators; limited agreement may increase measurement error and, consequently, affect the resulting estimates. Although no precise estimate can be made of the performance of a broader regional or national perspective, such perspectives serve as a baseline for these indicators, which have not previously been measured in Spanish hospitals. In addition, this set of indicators has been shown to identify opportunities for improvement in the hospitals studied, supporting their potential usefulness for other hospitals.
It is important to acknowledge the potential for evaluator bias, including a degree of subjectivity. For process indicators, the evaluators were external to the hospitals. Therefore, any potential bias may be more related to the evaluators’ own experience in retrieving the necessary data to measure the indicators. This aspect, however, can also be considered a strength, as it reflects the practical challenges of accessing the information required to assess service quality.
In contrast, for the management indicators, the data were provided by the heads of physical therapy departments, who are the end users of these indicators. The issue of whether quality assessment should be conducted internally or externally has long been debated.45,46,47 In this study, our main concern was not to externally judge the quality of each hospital, but rather to determine whether the necessary data to assess that quality could be obtained. Therefore, although the data on the management indicators may have been influenced by a certain subjectivity on the part of the supervisors of physical therapy, we believe that the results obtained reinforce the idea that the usefulness of any indicator lies not only in its conceptual validity, but also in the feasibility of its routine application by healthcare professionals within their own organizational environments.
Although the results of this study confirm the feasibility of using certain indicators, we cannot affirm their widespread use or applicability in all cases, and it is necessary to evaluate the implementation of adaptations tailored to particularities.
ConclusionOf the 22 quality indicators analyzed, 13 (9 clinical and 4 related to unit management) were found to be feasible and reliable. These indicators could be implemented immediately in hospitals within the Spanish National Health System to support continuous monitoring and identify opportunities for improvement in hospital-based physical therapy units. The remaining 9 indicators did not demonstrate sufficient inter-rater reliability or could not be adequately measured. Nonetheless, they may still hold value if adapted for local use to address specific challenges within individual healthcare settings.
ContributorsThe authorship of this article has been confirmed, with all authors having made substantial contributions, as outlined in the authors' guide. All authors were involved in the study's conception and design, drafting the article, critically revising its intellectual content, and approving the final version for publication. Data acquisition was conducted by authors 2 and 3, while data analysis and interpretation were performed by authors 1 and 4.
The author(s) declared no potential conflicts of interest.
The authors would like to give special thanks to Aurora Araujo Narváez, Antonio Jesús San Martín Caparros, and María del Mar Rodríguez Fresnillo in their capacity as hospital supervisors for their willingness and support in bringing this project to fruition. This study would not have been possible without them.
Acknowledgment is also due to the working group of supervisors who launched this project: Antonio San Martín, Francisco Rodríguez Jiménez, Juan Sánchez Garre, Juana María Cerdá Tomás, Manoli García Alcaraz, María de los Ángeles Martínez de Salazar Arboleas, María Encarnación Melgarejo González-Conde, María Isabel Novas Gutiérrez, Miguel Díaz Serrano, and Silvia Vázquez Giménez.
And finally, to the working group on hospital care in physical therapy of the quality commission of the Consejo General de Colegios de Fisioterapeutas de España (Spanish General Council of Colleges of Physiotherapists), which turns these projects into exciting endeavours.






