




Amyotrophic lateral sclerosis (ALS) is a neurodegenerative disease characterized by progressive muscle weakness. Falls are common and may lead to dependence, reduced quality of life, higher healthcare costs, and death. Few studies have examined falls in ALS.
ObjectivesTo investigate the frequency of falls in individuals with ALS with and without functional ambulation, and to identify predictors of falls at three and six months among those with functional ambulation.
MethodsA longitudinal prospective study included 66 individuals with ALS. Falls were assessed through interviews at three- and six-month follow-ups. Demographic and clinical characteristics, functional capacity, lower limb strength, fatigue, mobility, and balance were assessed. Descriptive, bivariate, and logistic regression analyses were performed.
ResultsAt baseline, 42 participants were ambulatory and 24 non ambulatory (wheelchair-dependent). Among ambulatory participants, 38 were assessed at three months (18 fallers, 47%) and 37 at six months (22 fallers, 59%). Among non-ambulatory participants, 22 were assessed at three months (4 fallers, 18%) and 20 at six months (2 fallers, 10%). Losses in both groups were due to death. Predictors of falls in the ambulatory group were lower limb strength (Odds Ratio [OR]: 0.844; p = 0.016) and fatigue (OR: 7.800; p = 0.037) at three months, and lower limb strength (OR: 0.856; p = 0.009) at six months.
ConclusionFalls can occur across functional profiles in ALS and are most frequent among ambulatory individuals. These findings highlight the importance of assessing fall risk and considering strategies. In ambulatory participants, interventions focusing on lower limb strength and fatigue may contribute to fall prevention.
Amyotrophic lateral sclerosis (ALS) is a neurodegenerative disease characterized by the loss of upper and lower motor neurons.1–3 Symptoms include motor aspects, such as muscle weakness and atrophy, general fatigue, dysphagia, speaking difficulties and respiratory dysfunction.1–3 and non-motor aspects, such as cognitive, psychiatric and autonomic disorders.1,2 The most common cause of death for people with ALS is respiratory failure.1–3
ALS is considered one of the most disabling chronic neurodegenerative diseases, as progressive generalized muscle weakness leads to activity limitations and participation restrictions. Falls are often reported in this population3,4 and can result in serious problems, such as pain, injury, the loss of confidence, dependence, a reduction in quality of life, an increase in healthcare costs and even death.3,5 The consequences of falls in individuals with degenerative diseases can exert strong impacts, leading to a cycle of disuse/dysfunction that accelerates the decline in muscle function and the loss of the ability to perform activities of daily living in an independent manner, such as standing and walking.6,7
Falls are considered multifactorial events, as the predictors of such events involve biological, behavioral, environmental and socioeconomic aspects.8 Some of the factors described as contributing to falls in ALS are muscle weakness, postural instability, mobility decline and changes in muscle tone.3,6 However, no studies have performed a broad investigation of the factors actually associated with the occurrence of falls in ALS. In a retrospective study on the occurrence of falls, a low correlation was found between falls and lower limb weakness.3 However, studies that prospectively investigate this outcome and potential predictors are needed for a better understanding of falls in ALS.
Falls can occur in individuals with different degrees of dysfunction from those with the capacity for independent walking in the community to those who rely on wheelchairs for mobility.7 However, the few studies that have investigated falls in ALS only analyzed individuals with the capacity for functional ambulation,3,6 leaving an important portion of people with ALS who have lost their functional ability to walk out of their analyses.
Investigating falls and associated factors, both in people with ALS with a functional gait and in people who only locomote in a wheelchair, is important to expand knowledge about the occurrence of falls in individuals with ALS. Such information can assist health professionals in the implementation of care and more effective fall prevention programs to improve wellbeing in this population. Therefore, the aim of this study was to investigate the frequency of falls in individuals with ALS with and without functional ambulation, and to identify predictors of falls at three and six months in the group with functional ambulation.
MethodsParticipantsSixty-six individuals with sporadic ALS, diagnosed according to the Awaji9 criteria and assisted between 2022 and 2023 at the Neuromuscular Disease Clinic, participated in the study. Exclusion criteria were: 1) medical history of another neurological disease or orthopedic surgeries; 2) cognitive impairment assessed by clinical judgment of the neurology team; 3) flail arm and leg variants for group homogeneity.2 This prospective longitudinal study was approved by the Human Research Ethics Committee (08661019.9.0000.5149). All patients voluntarily sign informed consent. Participants were classified into two mobility groups: functional ambulation (able to walk for household or community mobility, with or without assistive devices, including occasional wheelchair users) and non-functional ambulation (full-time wheelchair users).10,11
Sociodemographic and clinical characteristicsThe sociodemographic and clinical variables assessed were age, sex, schooling (years of study), time since diagnosis (years), site of the onset of the disease, use of Riluzole, history of falls in the previous six months (occurrence and number), need for locomotion-assistance device and if they had any home adaptations.
Outcome variableFallIn this study, a fall was defined as any event in which an unintentional movement to the floor or a lower level occurs, excluding intentional changes of position to rest on furniture, against walls or on other objects.12 Falls were assessed by an independent researcher, blinded to previous clinical testing and functional status, during the three-month and six-month follow-up visits.1 At each follow-up, participants were asked about the occurrence and number of falls since the previous visit. For each reported fall, information was collected on the need for medical care, hospitalizations, fractures, and any limitations in daily activities resulting from the event. Daily fall calendars or reminder calls were not used to avoid altering participants’ behavior, and motor and communication limitations in ALS made daily recording challenging. Participants were classified as fallers (when they reported at least one fall during the follow-up period) or non-fallers (when they reported none).
Predictor variablesFunctional assessmentFunctional status was assessed using a Brazilian version of Amyotrophic Lateral Sclerosis Functional Rating Scale-Revised (ALSFRS-R).13 The ALSFRS-R addresses 12 functional activities in four domains: a) bulbar function; b) gross motor function; c) fine motor function; d) respiratory function.11 Each function is scored ranging from 0 to 4.13 The total enables categorization in degrees of severity: mild (37–48 points), moderate (25–36 points) and severe (0–24 points).14
Muscle strengthMuscle strength was measured using the Medical Research Council (MRC) scale (0–5). Four muscles of the upper limbs (wrist extensors and flexors, elbow flexors and shoulder abductors) and four of the lower limbs (dorsiflexors, plantar flexors, knee extensor and hip flexors) were assessed bilaterally. These muscle groups were chosen due to the importance of their action and the ease of positioning individuals with ALS during the test. This assessment enabled calculating upper limb (score ranging from 0–40), lower limb (score ranging from 0–40) and global (sum of upper and lower limbs) muscle strength. The assessment of the muscle groups produced a score ranging from 0–80 for global muscle strength.15
FatigueThe Fatigue Severity Scale (FSS), Brazilian version, was used to assess general fatigue. The FSS is a nine-item self-report questionnaire used to investigate the severity of general fatigue in daily living. Each statement is attributed a score from 1 (strong disagreement) to 7 (strong agreement) points. The FSS score is obtained by the calculation of the average of all items. score of ≥ 4 indicates significant fatigue.16
Mobility and balance performanceMobility and balance were assessed only in participants with functional ambulation using the Brazilian version of Short Physical Performance Battery (SPPB). This battery consists of tests that assess balance (evaluated static balance in three standing positions), gait speed (usual gait speed) and five times sit-to-stand based on a time score. The total score is obtained from the sum of the results of the balance, gait speed and five times sit-to-stand tests and ranges from 0 (worst performance) to 12 points (best performance).17
Data analysisStatistical analyses were performed separately for participants with and without functional ambulation to account for their distinct clinical profiles. Normality was assessed using the Shapiro-Wilk test. Descriptive analyses were performed for baseline, three-month and six-month follow-ups in both groups. Within the functional ambulation group, an exploratory comparison between fallers and non-fallers was performed, followed by analyses to identify potential predictors of falls. Such analyses were not feasible in the group without functional ambulation because of the reduced number of participants and the lack of variability in fall outcomes. Binary logistic regression with stepwise forward method was performed to determine potential fall predictors at three and six months. To minimize overfitting, only clinically relevant variables3,6,7 or those with p < 0.20 in bivariate analyses were included, following recommendations relating predictors to the number of events18. A sensitivity analysis including age and sex was conducted (Supplementary Material). The logistic regression model at three-month follow-up included the independent variables: ALSFRS-R score, lower limb muscle strength, general fatigue, SPPB score and number of previous falls. At six-month follow-up the variables included were ALSFRS-R score, lower limb muscle strength, general fatigue and SPPB score. All prerequisites for regression analysis were met. Analyses were performed with SPSS (19.0; Chicago, IL, USA), with a 5% significance level.
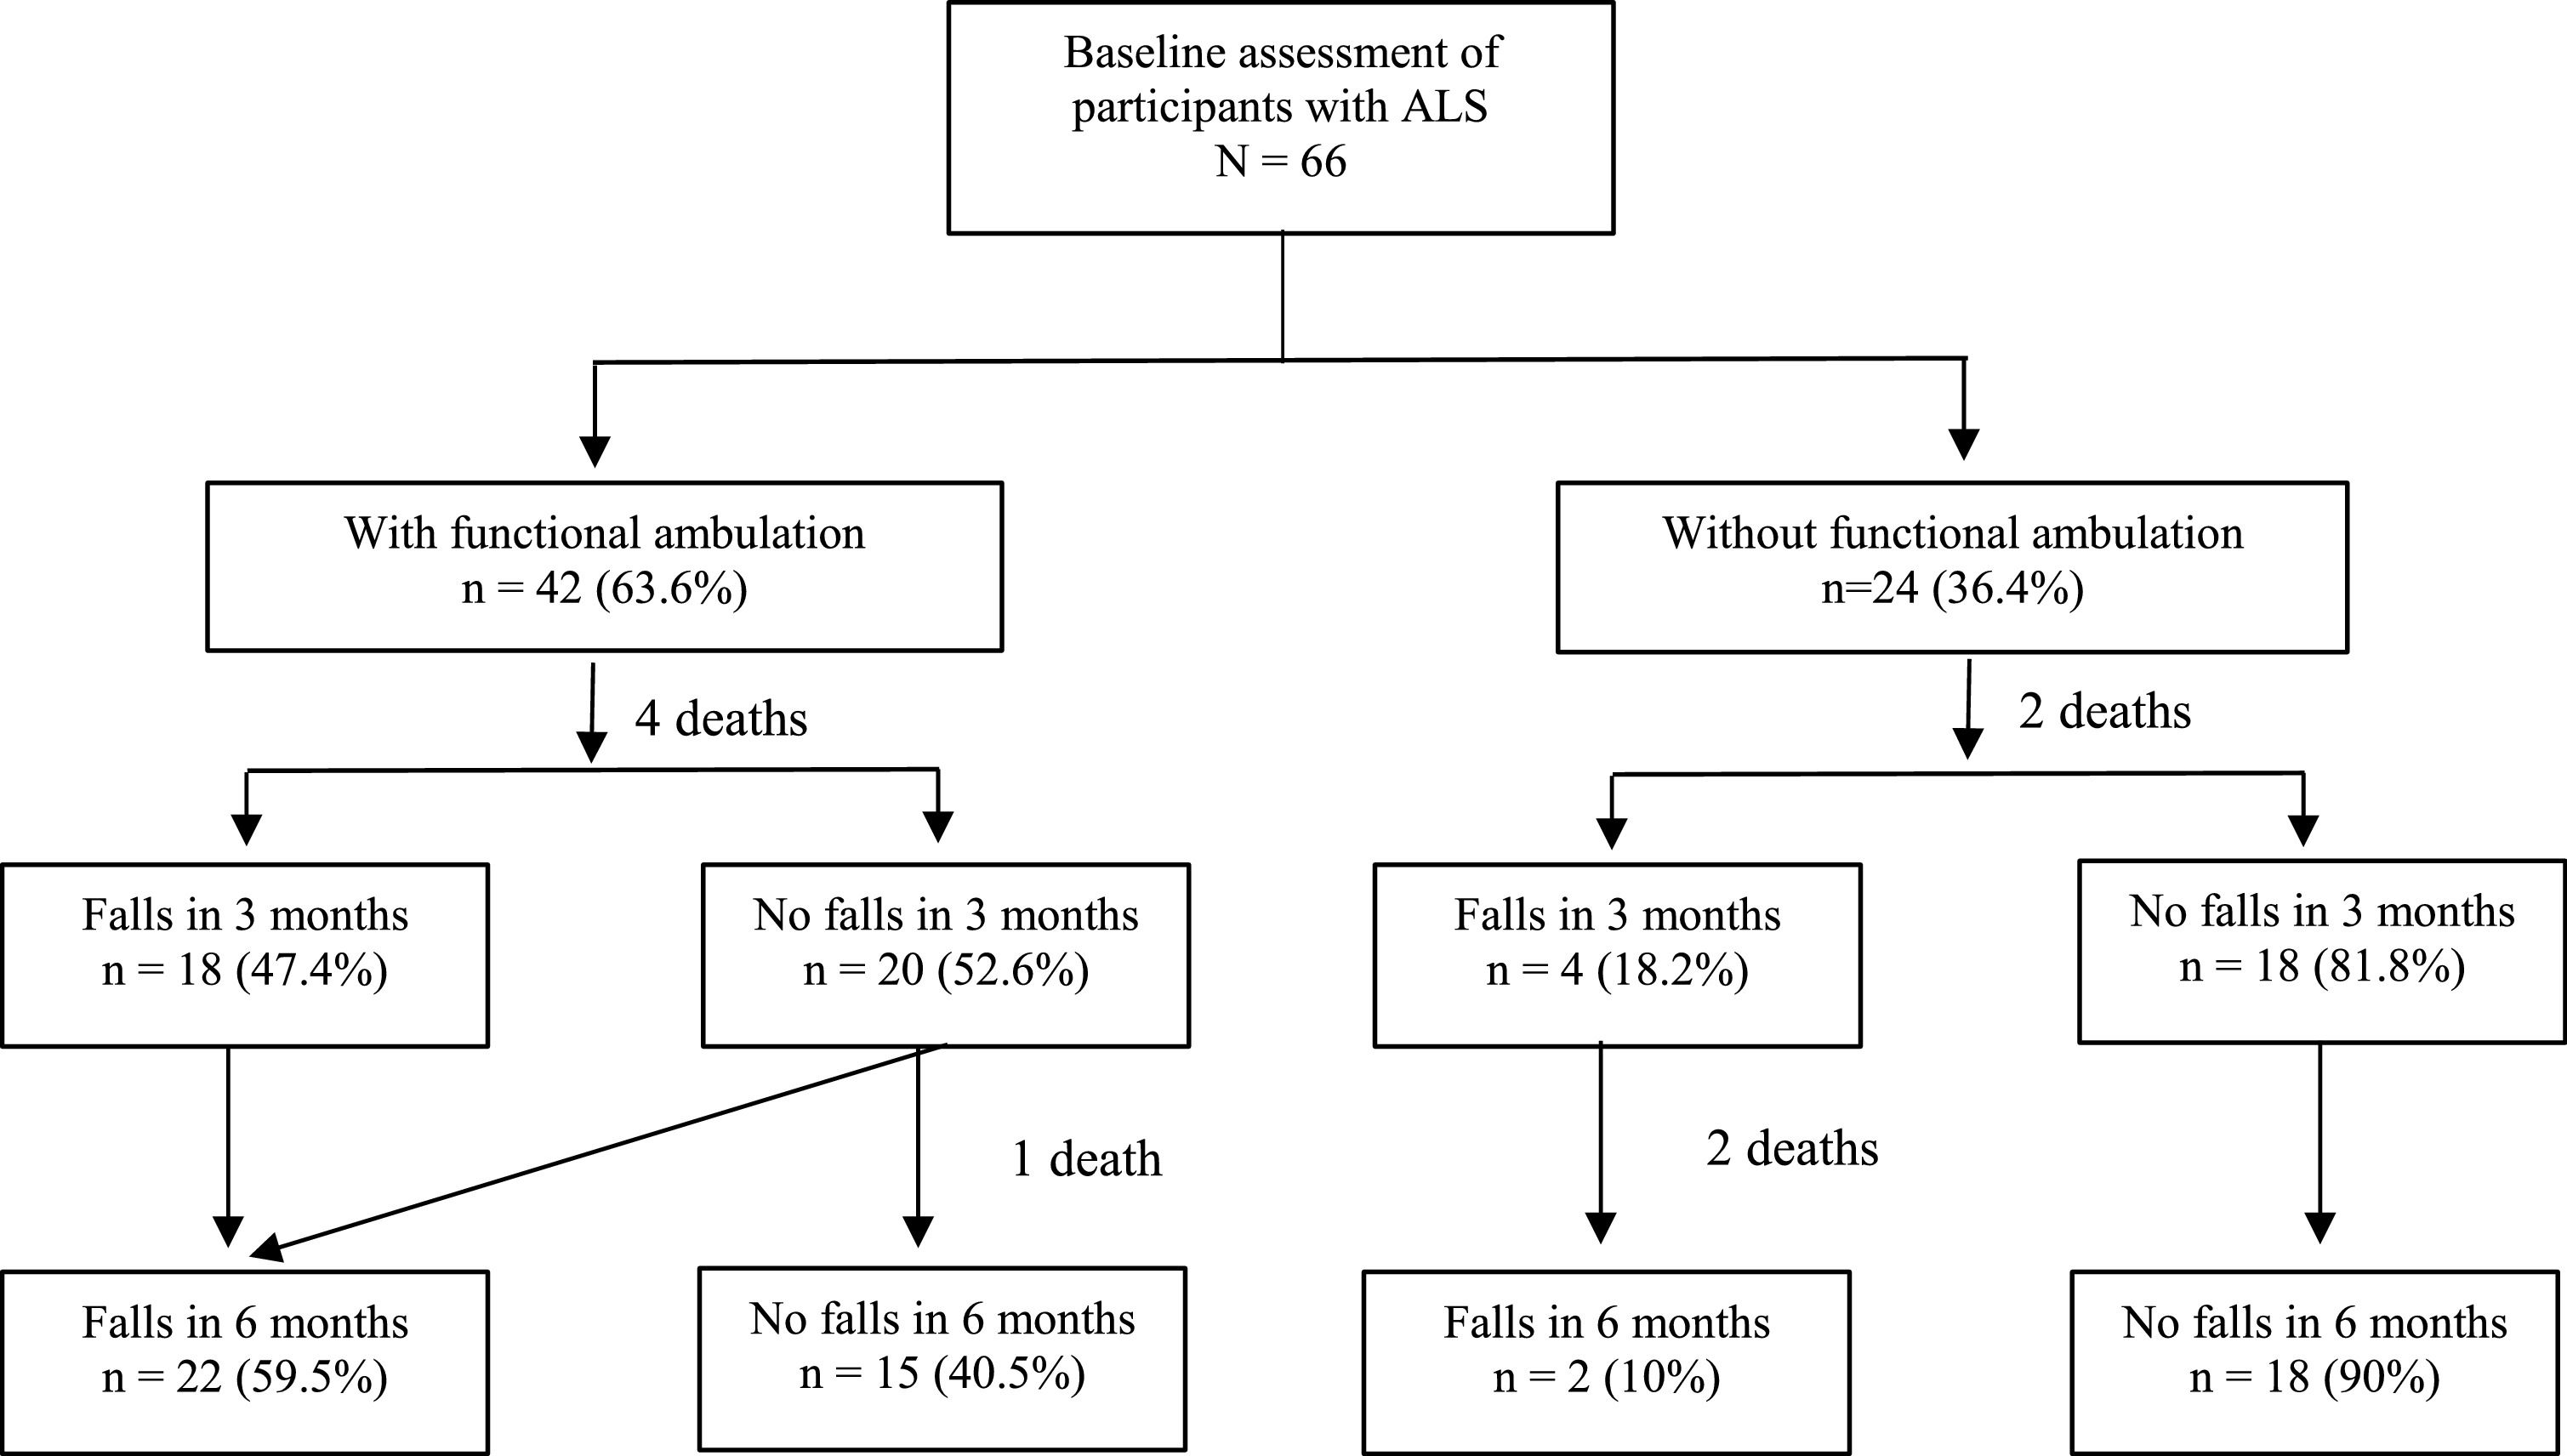
ResultsAmong the 66 participants in the study at baseline, nine died before the six-month follow-up and 86.4% completed the two follow-up stages. The participants who died between follow-ups were not included in the statistical analysis. At baseline, 63.6% of the participants had functional ambulation and 36.4% had non-functional ambulation. None of the participants with functional ambulation at baseline lost their ability to ambulate functionally at the three- and six-month follow-up (Fig. 1).
Falls and functional ambulation
Among the 38 individuals with functional ambulation, 47.4% reported at least one fall between baseline and the three-month follow-up, and 77.8% (n = 14) of these reported limitations in daily activities. The median number of falls was 1.0 (Interquartile Range [IQR]: 1.0–2.25; mean±SD: 2.39±2.64), with 38.8% (n = 7) experiencing recurrent falls. At six months, 37 individuals remained in the study. Of these, 59.5% reported at least one fall, and 63.6% (n = 14) of those reported limitations in daily activities. The median number of falls increased to 2 (IQR: 1.0–3.0; mean±SD: 3.82±4.88), with 54.5% (n = 12) experiencing recurrent falls. No participant reported the need for medical care or hospitalization and no fractures occurred due to the falls.
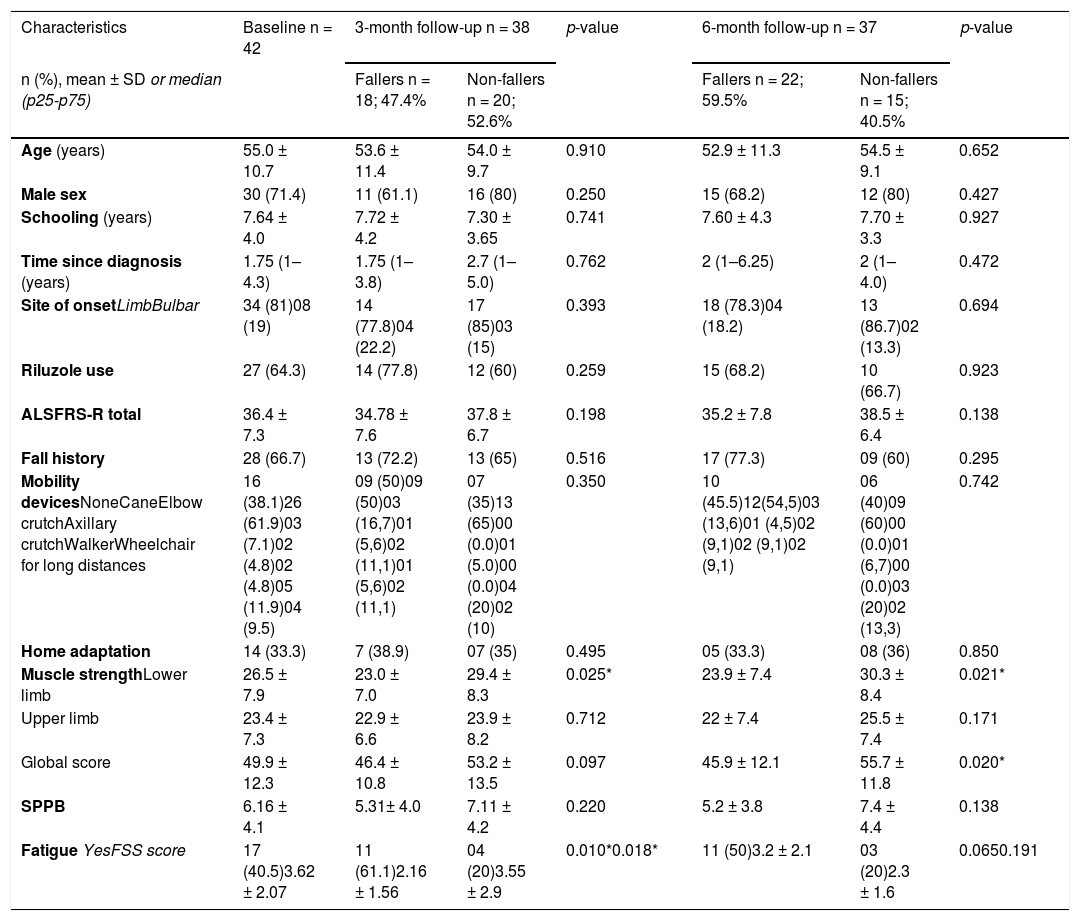
No significant differences were found between fallers and non-fallers with functional ambulation regarding age, sex, schooling, time since the diagnosis, functional status (ALSFRS-R) or mobility and balance (SPPB). Differences were found for lower limb strength and general fatigue at the three-month follow-up and lower limb strength at six-month follow-up. Participant characteristics and comparisons between fallers and non-fallers are shown in Table 1.
Characteristics of ambulatory individuals with amyotrophic lateral sclerosis (baseline, 3-month, and 6-month follow-up)”.
Abbreviations: n, number; SD, standard deviation; (p25-p75), interquartile range; ALSFRS-R, Amyotrophic Lateral Sclerosis Functional Rating Scale-Revised; m/s, meters per second; SPPB, Short Physical Performance Battery; FSS, Fatigue Severity Scale; * statistically significant.
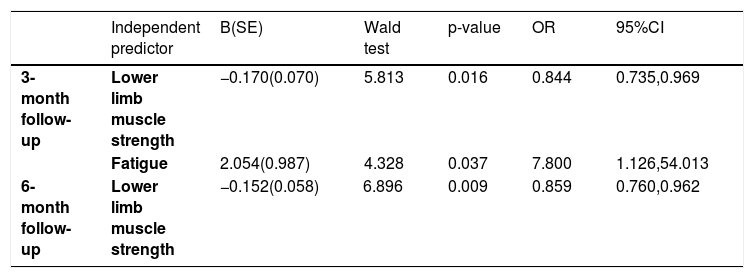
In the investigation of potential predictors of the occurrence of falls in individuals with ALS with functional ambulation, the predictors of falls at three months were lower limb muscle strength (OR:0.844; p = 0.016) and general fatigue (OR:7.800; p = 0.037). A 16% increase in the odds of the occurrence of a fall in three months was expected for each point reduction in the lower limb muscle strength score. The occurrence of fatigue increased the odds of falling in the subsequent three months 7.8 times (Table 2). No significant associations were found for the other variables in the regression analysis (ALSFRS-R score, SPPB score and number of previous falls) and these variables were not included in the final model.
Independent predictors of falls at three and six months among participants with functional ambulation (final binary logistic regression model).
Abbreviations: B, estimated coefficient; SE, standard error; OR, odds ratio; CI, confidence interval.
Only lower limb muscle strength (OR:0.859; p = 0.009) was a predictor of falls at the six-month follow-up. A 14% increase in the odds of the occurrence of a fall in six months was expected for each point reduction in the lower limb muscle strength score. No significant associations were found for the other variables in the binary logistic regression analysis (ALSFRS-R score, general fatigue and SPPB score) and these variables were not included in the final model (Table 2).
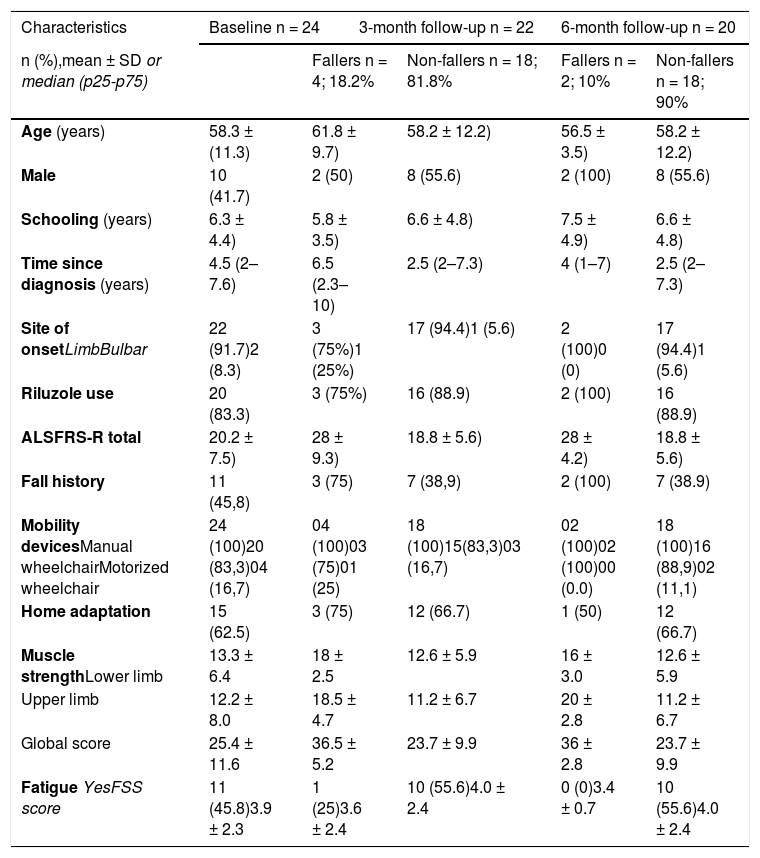
Falls and non-functional ambulationAt baseline, 24 individuals did not have functional ambulation, of whom 22 were assessed at the three-month follow-up. Most participants (81.8%) reported no falls during this period. Among the 18.2% (n = 4) who experienced falls, the median number of falls was one (IQR: 1.0–1.75; mean±SD: 1.25±0.5). Only one individual reported needing to seek medical care and be hospitalized due to fracture. Two participants (50%) reported limiting their activities due to the fall. At the six-month follow-up, 20 individuals were assessed, and only two reported falls during this period, with a median of 1.5 falls (IQR: 1.0–2.0; mean±SD: 1.50±0.71). None of the participants who reported no falls at the three-month follow-up experienced any falls during the subsequent period. Thus, the participants remained in the same faller and non-faller groups throughout the entire follow-up period. Due to the small sample size, no comparative analysis between fallers and non-fallers was performed, and neither was the analysis to determine predictors of falls among the individuals with non-functional ambulation. The descriptive analysis of this group is displayed in Table 3.
Characteristics of non-ambulatory individuals with amyotrophic lateral sclerosis (baseline, 3-month, and 6-month follow-up).
Abbreviations: n, number; SD, standard deviation; (p25-p75), interquartile range; ALSFRS-R, Amyotrophic Lateral Sclerosis Functional Rating Scale-Revised; FSS, Fatigue Severity Scale.
To the best of our knowledge, this study is among the first to investigate the frequency of falls in individuals with ALS, both with and without functional ambulation, and to identify predictors of falls specifically among those capable of functional ambulation. Falls have been observed in both walkers and wheelchair users. The predictors of falls between baseline and the three-month follow-up among those with functional ambulation were lower limb strength and general fatigue, whereas only lower limb strength was a predictor of falls at the six-month follow-up. It was not possible to identify predictors of falls among those without functional ambulation due to the small sample size. Further research on falls in ALS patients should include those without functional ambulation to identify predictors. The rate of falls among the participants with functional ambulation was greater than that among the non-ambulators at both the three-month (47.4%vs 18.2%) and six-month (59.5%vs 10.0%) follow-up, as expected. Individuals with ALS capable of functional ambulation are more exposed to situations that increase the odds of falling, as they are still capable of performing activities that involve walking, transfers and the maintenance of the standing position.4,19 Studies comparing falls among ambulators and non-ambulators with other neurological conditions, such as multiple sclerosis and spinal cord injury, also report a greater frequency of falls among those with the capacity to walk.8,19,20
Falls are frequently reported during clinical appointments and are considered an adverse outcome in ALS clinical trials. However, the actual occurrence of falls in this population is still not well characterized. The mean number of falls observed in the present study (2.39±2.64) was lower than that reported in a previous study (5.46±8.56 falls).3 This difference may reflect variations in participants’ functional profiles, as that study included only individuals capable of walking independently for at least 20 feet (6.1 m).3 A notable finding of the present study was that the number of falls increased over the follow-up period in both groups, indicating recurrent falls over time. These findings highlight the importance of implementing prevention strategies tailored to individual needs7 to reduce the risk of new fall episodes, morbidity, and mortality in this population.21 Further studies are needed to investigate the frequency and recurrence of falls in individuals with different functional conditions and populations to better understand this outcome in ALS.
Among participants who fell, limitations in daily activities were commonly reported in both ambulatory and non-ambulatory individuals. This outcome may be related to reduced confidence and an increased fear of falling, which may lead to a further mobility restrictions and greater dependence in daily activities.20,22 In individuals with ALS, reduced activity can be particularly debilitating, as the weakness from inactivity adds to the progressive loss of strength caused by the disease.23 Prolonged inactivity may result in muscle atrophy, shortening, joint stiffness, and osteoporosis, increasing the risk of contractures, pain, and fractures.23 Therefore, research into strategies to prevent falls and minimize their functional impact is essential.
Despite the frequency of falls, none of the ambulatory participants required medical care due to a fall, whereas a fracture requiring medical attention occurred in the non-ambulatory group. Similar findings have been reported in other neurological populations, such as spinal cord injury and multiple sclerosis, where ambulators sustained milder injuries and required less medical care despite more frequent falls.8,19,20 The significant dysfunction and limitations of ALS among individuals who have lost the ability to walk make them more vulnerable, as they are likely to be less able to react to protect themselves in a fall (i.e., reduce control of the fall by activating muscles or using the upper limbs), resulting in more severe injuries.19,20 Minor injuries not requiring medical attention (e.g., bruises or scratches) were not systematically collected in this study, which could be considered in future investigations.
Among individuals with functional ambulation, the predictors of falls were lower limb muscle strength and the presence of fatigue at three months, whereas only lower limb muscle strength remained a predictor at six months. These results confirm the previously identified association between lower limb strength and falls in individuals with ALS.3 This association is well established and has also been reported in other populations and diagnostic groups.22,24 Muscle activation is required to move, stabilize, and balance the body; insufficient strength increases fall risk. Therefore, an inability to produce enough strength increases susceptibility to falling. In the present study, each unit reduction in the lower limb muscle strength score increased the odds of falling by 16% in three months and by 14% in six months. The progressive decline in muscle strength is unavoidable in individuals with ALS, as the disease is characterized by the continuous degeneration of motor neurons throughout the nervous system.1,2 ALS begins as a focal process and gradually spreads to different body regions.1,2 Beyond disease-related weakness, ALS patients lose strength due to disuse, especially in unaffected muscles, and often adopt a sedentary lifestyle.10,23,25 Even those who remain ambulatory tend to adopt a more sedentary lifestyle as an adaptation to the challenges imposed by the disease. Barriers to activity include walking risks, fear, deconditioning, weakness, and fatigue.11
Although the course of ALS cannot be modified, several studies have reported beneficial effects of physical training on maintaining or improving muscle strength, especially during the early stages of the disease.10,23,25,26 Strength maintenance and even gains may occur in affected muscles through compensatory mechanisms such as collateral sprouting of surviving motor neurons. However, as motor units are progressively lost, the adaptive capacity to training declines, and positive effects are limited to the initial disease stages.10,23,25,26 Therefore, considering the finding of a reduction in lower limb strength as a predictor of falls, future studies should investigate whether interventions for improving strength can reduce the occurrence of falls in this population.
In the present study, general fatigue increased the odds of falling 7.8 times among individuals with functional ambulation in the three months following the initial assessment. Fatigue is a disabling symptom that has also been considered a predictor of falls in other populations, such as patients with multiple sclerosis27 and Parkinson’s disease.28 Although fatigue is a frequent symptom in ALS, it remains poorly understood, investigated and treated clinically.23,29 Recent evidence from a Brazilian cohort supports the multidimensional nature of fatigue in ALS.30 reinforcing its multifactorial etiology.29,30 Fatigue in ALS manifests as general fatigue, experienced as generalized tiredness or lethargy, and physical fatigue, characterized by an objective decline in muscle force capacity.29 The perception of fatigue in ALS tends to worsen throughout the day and exerts an impact on the motivation to perform simple tasks due to the considerable need of effort and low performance.29 Fatigue in ALS reduces strength and functioning, affecting daily activities, quality of life, 29 and participation, highlighting the importance of addressing fatigue in rehabilitation. In this study, fatigue predicted falls only between baseline and the three-month follow-up (shorter follow-up period). The wide variation in the perception and intensity of fatigue over time, influenced by factors such as respiratory function, medication use, nutrition, activity level, and psychological aspects, may have contributed to this finding. 29 This highlights the complexity of fatigue in ALS and reinforces the need for further research on this symptom.
The present study contributes to the longitudinal investigation of falls in ALS by including individuals both with and without functional ambulation and evaluating potential predictors specifically in the functional ambulation group. However, this study has limitations. A convenience sample of ALS patients from a single neuromuscular diseases reference clinic limited the overall sample size. The small number of participants in the non-functional ambulation group made it impossible to perform predictive analyses. In the functional ambulation group, the relatively small number of fall events may have limited statistical power and restricted the number of predictors that could be included in the multivariate regression model. Although larger studies are needed to confirm these findings, longitudinal research in ALS remains challenging due to the disease’s rarity, short survival, and heterogeneity. Nevertheless, this study is the first to investigate falls longitudinally in individuals with ALS, providing valuable insights into potential predictors of this outcome. Other variables, such as age, which is frequently reported as a determinant of fall risk in other populations, were not included, as the age distribution was similar between fallers and non-fallers. However, future studies should investigate whether age contributes to fall risk in ALS or whether disease-related weakness predominates. The fall monitoring method used during follow-up also represents a limitation, and future studies may benefit from more frequent monitoring, such as fall diaries. Another limitation is that cognitive status was evaluated through routine clinical judgment by the neurology team, rather than through a standardized cognitive screening instrument. This approach reflects common clinical practice in ALS care, particularly in motor-focused studies. However, incorporating validated ALS-specific cognitive screening tools in future research could improve diagnostic precision and enhance comparability across cohorts. Future research should further investigate factors related to falls in ALS, including recurrent and injurious falls, as well as the potential influence of non-motor symptoms such as cognitive dysfunctions.
ConclusionFalls can occur across different functional profiles in ALS but are most frequent among ambulatory individuals. These findings highlight the importance of assessing fall risk and implementing preventive strategies. In ambulatory individuals, interventions should target fatigue and lower limb strength early in rehabilitation to help prevent falls. Future studies should also consider individuals with ALS without functional ambulation.
FundingThis research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
The authors declare no conflicts of interest.
The authors thank all participants and their families. We also thank the University Hospital of Federal University of Minas Gerais (Hospital das Clínicas da UFMG) for the support in the realization of this work. The authors also are grateful for the support provided by Pró-Reitoria de Extensão (PROEX/UFMG) from Brazil.






